Mayo Clinic researchers report encouraging results using a new radiation technique called minibeam radiotherapy to treat patients with treatment-resistant cancers in or near the skin. The technique delivers very high doses of radiation through closely spaced, extremely narrow beams while limiting radiation exposure to healthy tissue between the beams.
In a study published in the International Journal of Radiation Oncology, Biology, Physics, researchers found symptoms improved in 86% of patients. Among 40 tumors evaluated, 22.5% disappeared, 25% shrank and 45% remained stable.
"What's encouraging is that patients were able to tolerate these higher radiation doses, even though many had cancers that had resisted previous treatments," says Michael Grams, Ph.D., co-first author of the study and radiation oncology medical physicist at Mayo Clinic Comprehensive Cancer Center. "We're also seeing evidence that this type of radiation may work together with the body's immune system. That could give us another way to approach difficult-to-treat cancers."
The findings suggest that minibeam radiotherapy may do more than change how radiation is delivered. It also may affect tumor biology.
Rethinking how radiation is delivered
Conventional radiation therapy aims to deliver enough radiation to destroy cancer cells while limiting damage to surrounding healthy tissue. Advances in technology have made it possible to target tumors with increasing precision.
"Tumors that require high doses of radiation and have infiltrated sensitive parts of the body provide the most formidable challenge for us. Ideally, we could treat the tumor and preserve function," says Scott Lester, M.D., co-author and a radiation oncologist at Mayo Clinic Comprehensive Cancer Center. "We want to eliminate the cancer and simultaneously promote healing to get the best functional outcome for our patients."
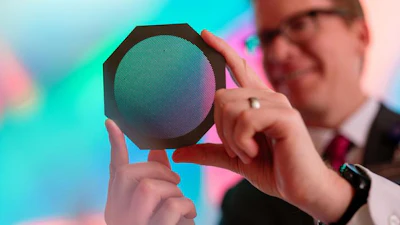
Mayo Clinic researchers began studying minibeam radiotherapy five years ago, building on preclinical research. They developed a device called a tungsten collimator that divides a conventional radiation beam into 0.5-millimeter beamlets spaced 1 millimeter apart from center to center.
The resulting pattern creates areas of high radiation exposure, or "peaks," separated by areas of low exposure, or "valleys." Researchers believe this pattern allows healthy tissue to repair and regenerate more effectively than with conventional radiation therapy. "The treatment can also be completed in two or three sessions instead of 10 to 30 sessions, making it particularly meaningful to patients," says Dr. Grams.
Studying minibeam radiotherapy in patients for the first time
The clinical trial treated 36 patients with 46 tumors, 40 of which could be evaluated. Patients had advanced skin cancers, including melanoma and squamous cell carcinoma, or soft tissue sarcomas. Ninety percent of patients had received at least two previous cancer therapies, and all tumors had been resistant to other treatments.
Of the 46 tumors, 39 tumors (85%) were treated with minibeam radiotherapy alone, while seven (15%) also received planned conventional radiation therapy.
At a median follow-up of about 15 months, 22.5% of evaluable tumors had disappeared, 25% had shrunk and 45% remained stable. At 12 months, the estimated local control rate — meaning the cancer had not progressed in the treated area — was 89% overall and 92% among tumors receiving minibeam radiotherapy alone.
Patients also experienced substantial symptom relief.
"The study suggested a compelling benefit to quality of life for patients, from relief from pain and bleeding to restoring daily physical functions," says Kimi Chauhan, M.D., a resident in radiation oncology at Mayo Clinic and co-first author of the study.
Patients experienced fewer radiation-related side effects than typically seen with conventional radiation despite receiving higher radiation doses. "The treatment appears to support tissue healing while attacking cancer, making it particularly relevant for complex cases where conventional options are limited," says Dr. Lester.
Understanding the immune response
Researchers also observed an unexpected finding that raises questions about how minibeam radiotherapy may interact with the immune system.
In 11% of patients, cancer outside the area treated with minibeam radiation also responded, even though patients received no other cancer treatments. This phenomenon, known as an abscopal response, can occur when radiation delivered to one tumor is associated with a response in cancer elsewhere in the body.
"This represents an important shift in how we think about radiotherapy because our results suggest that you don't necessarily need to treat all of the tumor with an ablative dose," says Robert Mutter, M.D., chair of research in the Department of Radiation Oncology and co-leader of the Novel Therapeutics and Therapeutic Modalities Research Program at Mayo Clinic Comprehensive Cancer Center. "We may be able to exploit the distinct ways that tumors die after minibeam radiotherapy to personalize treatment and activate the immune system to fight the cancer."
What's next for minibeam radiotherapy research
Researchers are conducting laboratory studies to better understand the mechanisms that trigger the immune response and which patients are most likely to benefit. An ongoing phase 1 clinical trial is testing increasing doses of minibeam radiotherapy. The team is also developing studies investigating its use in early-stage breast cancer in combination with immunotherapy and during surgery for unresectable pancreatic cancer.
"Minibeam radiotherapy gives us another potential treatment tool for complex cancers," says Dr. Grams. "The goal is now to understand where it can have the greatest impact for patients."
For more information, funding and authors, read the study.