Nearly 70,000 Americans died of a drug overdose in 2025. While that is a decline from the nearly 108,000 deaths recorded in 2022, these grim figures distinguish the U.S. from other high-income countries. At the peak of the opioid crisis, the U.S. overdose death rate was 68% higher than Canada's and nearly five times that of Australia.
And death is only the starkest indicator: Substance use disorder imposes hundreds of billions of dollars in healthcare, criminal justice and lost productivity costs each year – to say nothing of the incalculable disruption to families and communities.
For decades, U.S. drug policy has aimed to reduce drug use by disrupting supply, punishing possession and use, and promoting abstinence.
But this isn't the only approach to addressing drug use.
2026 marks the 25th anniversary of Portugal's landmark decision to decriminalize the possession of all drugs for personal use. This is one of the world's longest-running efforts to center public health and harm reduction in national drug policy.
As a criminologist and a political scientist, we have spent the past three years teaching a course on drug policy and harm reduction in Portugal, bringing dozens of students to the country to study its approach firsthand. That experience has given us a close look at both the promise and the limitations of the Portuguese model.
Surprising assumptions
While in Portugal, our students meet with policymakers, health and law enforcement officials, treatment providers and practitioners. These experiences complement our research on how policies once considered unthinkable can gain acceptance among the public and policymakers. We also examine nonpunitive approaches to problematic drug use – that is, recurrent drug use that significantly interferes with a person's health or quality of life.
What always strikes us in our work here are the pragmatic and, compared with the U.S., surprisingly apolitical assumptions that underlie Portugal's approach: People will use drugs, and public policy can reduce the harms associated with that use even when it cannot entirely prevent it.
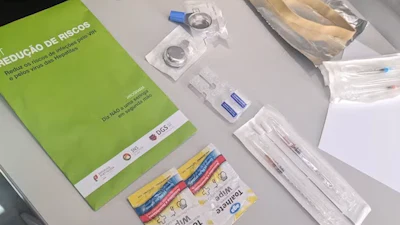
In practice, this means measures such as providing sterile equipment to consume drugs, expanding harm-reduction services that can help people better understand the substances they are using, and operating overdose prevention sites where substances can be used under medical supervision.
These measures do not treat drug use as harmless, nor do they abandon recovery as a goal. Instead, they recognize that reducing harm has value in itself, and that keeping people alive and healthy can be the first step on a path away from disordered use.
A devastating problem
Portugal embraced this approach during a devastating heroin crisis in the late 1990s. Injection drug use was fueling one of Europe's worst HIV epidemics, while problematic drug use was felt in Portuguese communities across social and economic lines.
At that time, an estimated 1% of the population was addicted to heroin, with overdose deaths rising sharply. By the turn of the century, Portugal had the highest HIV incidence in the European Union among people who injected drugs.
Even before formal decriminalization, police, healthcare professionals and other workers who came into contact with people using drugs had already begun directing them away from punishment and toward care. These emerging practices soon became the basis for a broader national response.
In 1998, the Portuguese government appointed a multidisciplinary commission of experts, including physicians, psychiatrists, psychologists, legal experts and researchers, to rethink the country's drug policy. Its recommendations became the basis for a national strategy integrating prevention, treatment, harm reduction and social reintegration that was adopted in 1999, followed by decriminalization in 2001.
Decriminalization does not mean that possession simply goes unaddressed: People found to have small amounts of substances for personal use can be referred to multidisciplinary dissuasion commissions, which can connect them with services or impose minor administrative sanctions. But they cannot be criminally charged or incarcerated for possession.
Drug manufacturing and trafficking, meanwhile, remain criminal offenses.
Portugal's financial investment in this strategy has remained in place despite financial crises and budget cuts. The country continues to provide multiple ways for people who use substances to access healthcare and treatment, while also addressing problems such as housing and unemployment that can make sustained recovery difficult.
Dramatic results
The results have been striking. Drug-related deaths fell sharply as Portugal adopted its new approach, and they remain low by European standards. In 2023, Portugal recorded 105 fatal drug overdoses, up slightly from 96 the previous year and 81 in 2021, but still far below the levels seen at the height of the country's drug crisis.
New HIV diagnoses associated with injection drug use, which still numbered in the hundreds annually in the mid-2000s, fell from 583 in 2005 to just 19 in 2024, a decline of roughly 97%.
Treatment also remains central to the Portuguese model: In 2023, more than 24,000 people received care through the country's specialized public outpatient system. This system consists of a nationwide network of multidisciplinary treatment teams providing medical care and connections to other health and social services. The use of cannabis – which, like all drugs in Portugal, is illegal though not a criminal offense – is now one of the leading reasons people enter this system.
Portugal also experienced a broader shift in how problematic drug use was publicly understood. Although the Portuguese still hold negative views of substance use, problematic use increasingly came to be understood as a health and social problem rather than a moral failing warranting punishment.
An international model – or one of a kind?
These outcomes helped turn Portugal into an international model for drug policy reform. But its experience has proven easier to admire than to replicate.
More recent experiments underscore a less celebrated lesson from Portugal: These policies depend on an integrated system of health and social services, sustained political support and buy-in from the institutions, including law enforcement, charged with making them work.
British Columbia's 2023 decriminalization pilot offers a more complicated example and an important contrast with Portugal. Despite Canada's universal healthcare system and an established harm-reduction infrastructure, the province did not replicate Portugal's integrated model. Police were not required to refer people to services, treatment providers received no additional funding, and waitlists persisted.
The three-year pilot sharply reduced possession offenses and police drug seizures, but there was little evidence of broader health benefits. Amid growing concerns about public drug use, the province allowed the experiment to expire in January 2026.
If British Columbia illustrates the limits of reform even with a comparatively robust public health system, Oregon's experience illustrates the risks of pursuing such a strategy without one.
In Oregon, voters approved Measure 110 in 2020, decriminalizing drug possession while directing cannabis tax revenue toward expanded treatment and recovery services. But a December 2025 state audit concluded that implementation was plagued by unstable leadership, delayed services and poor coordination.
Unlike Portugal, and to a lesser extent British Columbia, Oregon also failed to secure buy-in from law enforcement, leaving many officers opposed to the policy and skeptical of their role in implementing it.
Rather than creating an integrated system of care, new services often operated alongside the state's already fragmented behavioral health system. Meanwhile, highly visible drug use, rising fentanyl deaths and a citation system that rarely connected people to treatment fueled public frustration and political pressure to reverse the course.
Oregon lawmakers recriminalized possession in 2024, before the state had even developed reliable data to assess whether the experiment had improved access to care or reduced drug-related harms.
Building a sustainable policy
Twenty-five years on, Portugal's most important lesson may not be about decriminalization itself. Rather, its experience shows that reducing the harms of drug use requires painstakingly building and sustaining a system that connects people with treatment, healthcare and social support without making abstinence a precondition for receiving help.
Changing drug laws can be part of that project. The harder work is building and sustaining the institutions that make a public health approach possible.